Thursday, February 26, 2015
Anatomy of the Clavicle
Other names for Clavicle are:
Collar bone,Beauty bone
The shoulder is the most freely moveable joint in the body. The extreme range of its possible movements makes the shoulder joint susceptible to dislocation. One of the bones that meet at the shoulder is the clavicle, which is also known as the collarbone. The collarbone is long, curvy, and located at the root of the neck. One of the main functions of the collarbone is to hold the arms freely and supported, away from the trunk. Fractures of the collarbone are common. A fracture is easy to detect because the clavicle lies directly under the skin, making any deformity immediately visible. Symptoms of a fractured collarbone include tenderness, swelling, and an inability to move the arm because of pain. The victim may also have the desire to hold the arm against the chest to stabilize it. It is common practice to apply a sling to stabilize the fracture, allowing it to mend. Extreme fractures may require surgery to pin the collarbone back together.
Clavicle canbe divided into a cylindrical part called the shaft, and two ends – medial (sternal end) and lateral (acromial end).
Structure of the Clavicle
The clavicle consists of cancellous tissue, enveloped by a compact layer, which is much thicker in the intermediate part than at the extremities of the bone. 11
Functions of clavicle
- The Clavicle allows the scapula to move freely on the thoracic wall due to the way in which it acts as a rigid support for the scapula and the arm. This gives the arm a higher range of movement.
- The collar bone protects the neurovascular bundle that supplies the upper limb.
- The Clavicle acts as a shock absorber by transmitting physical impacts from the upper limb to the axial skeleton.
Lateral 1/3:
Trapezius muscle,
Deltoid Muscle,
Coracoclavicular ligament.
Medial 1/3:
Sternocleidomastoid muscle,
Pectoralis major muscle,
Subclavius muscle,
Costoclavicular ligament.
Ossification of the Clavicle
The clavicle is the first bone in the human body to ossify. The ossification process is of two types - intramembranous or dermal and endochondral. ; it is ossified from three centers—viz., two primary centers, a medial and a lateral, for the body, 53 which appear during the fifth or sixth week of fetal life; and a secondary center for the sternal end, which appears about the eighteenth or twentieth year, and unites with the rest of the bone about the twenty-fifth year.
Articulations of the Clavicle
The clavicle articulates with three bones: the sternum, the scapula, and the first rib. The sternal extremity forms an ovoid articular facet that sits in the clavicular notch of the manubrium. Just inferior to this facet is a smaller oval surface for articulation with the costal cartilage of the first rib. Laterally, an oval facet on the inferior aspect of the acromial extremity articulates with the acromion of the scapula.
Gender Variations of the Clavicle
Female clavicle is shorter, lighter, thinner, smoother, and less curved than in males . The lateral end of the clavicle is a little below the medial end in females whereas In males, the lateral end is either at the same level or slightly higher than the medial end.
Borders of the Clavicle
The anterior border is concave, thin, and rough, and gives attachment to the Deltoideus. The posterior border is convex, rough, thicker than the anterior, and gives attachment to the Trapezius.
Surfaces of the Clavicle
- The anterior surface- It is convex forwards,gives origin to pectoralis major
- The posterior surface- It is thickened and smooth,gives origin to sternohyoid muscle
- The superior surface- This surface iss rough in its medial part.
- The inferior surface- It has a rough oval impression at the medial end. It harbors a longtitudinal groove called subclavian groove in its lateral half,gives attachment to subclavius muscle
- Lateral (Acromial) End:articulates with with the acromian process of the scapula to form the acromioclavicular joint
- Medial (Sternal) End:articulates with the clavicular notch of the manubrium sterni to form sternoclavicular joint


READ MORE ABOUT:
Anatomy of the Scapula
Anatomy of the Clavicle
Sternum anatomy
Shoulder Anatomy
Sterno-Clavicular Joint Anatomy

What Could Be The Cause Of Swelling On Face
The swelling on face or facial edema should be taken seriously if there is no history of insect bite, wasp sting or honey bee sting and when it is after a throat infection. The swelling on face or facial edema could be due to renal disorder (kidney disease). If on routine examination of urine of the patient, excretion of albumin or protein is detected; there is a need to consult a nephrologist for proper investigations. Blood biochemistry for blood urea, serum creatinine, serum proteins, serum electrophoresis, urine electrophoresis and 24-hour urinary protein should be done. Excretion of protein in 24-hours through urine will help the physician to assess the loss of proteins and possible course of action. Urine electrophoresis would show the type of protein being excreted in the urine. In a patient with nephrotic syndrome, serum electrophoresis would show hypoalbuminemia (low level of albumin in blood), hypogammaglobulinemia (low level of globulins in blood) and raised alpha-2 (a-2) globulin, and urine electrophoresis may show albuminuria (excretion of albumin in urine) or non-selective proteinuria (excretion of almost all the fractions of serum proteins in urine). Total serum protein and its fractions like albumin and globulin would show the altered albumin-globulin ratio. The normal albumin-globulin ratio (Albumin/Globulin) is 3:1 and it may be reversed in patients with swelling on face due to kidney disease.
The swelling on face or facial edema is directly associated with albuminuria (excretion of albumin in urine) and salt retention. The loss of blood albumin through urine hinders the return of fluid from the tissues into the blood and may thus lead to development of edema. It is well known that 68 to 70% weight of our body is due to water content in the blood and tissues. Around 12 to 14% of the total water volume of our body is in the blood and the rest is present in the tissues of the body. There is direct correlation between albuminuria (excretion of albumin in urine) and edema. Retention of Chloride is also a common accompaniment of edema.
However, there may not be any retention of Chloride in majority of the cases with edema. The edema is perhaps the greatest problem confronting the students of nephrology. Pathological lesions in the kidney need to be evaluated microscopically through renal biopsy examination. Blood urea and serum creatinine may be normal. There may be salt retention without edema and edema without salt retention. The Chloride may collect in watery subcutaneous tissue due to some external factors also without involvement of any renal lesion.
Two forms of swelling on face or facial edema could be recognized and these are called nephritic edema and nephrotic edema. In nephritic edema the protein content of the edema fluid is over 1 gram/dl whereas in nephrotic edema the protein content of the edema fluid is always less than 0.1 gram/dl. Nephritic edema occurs in acute glomerulonephritis. The capillaries in the subcutaneous tissue become more permeable leading to leakage of proteins in the extra cellular fluid. Nephrotic edema occurs in the wet nephritis or second stage of nephritis, in nephrosis and also in renal amyloidosis. The edema is caused due to the great fall in the osmotic pressure of the blood due to constant loss of protein in urine; so, the fluid from the blood vessels escapes into the tissues in an effort to correct the viscosity of blood plasma.
New Workshop Scheduled! Anatomical Landmarks of the Anterior Torso

This workshop will focus on anatomy of anterior torso, which includes rib cage, clavicular, and sternal features and well as muscles of the chest and abdomen. It will be held on February 23 from 9:30 a.m. until 12:30 p.m. (Again, coffee is available just a few doors down!) We will have a fantastic model with a very defined physique.
For more information about this workshop series, check out the original post about it.
The Palette and Chisel is located at 1012 N. Dearborn in Chicago. It is easily accessible from either the red or brown el trains and from the CTA bus. Parking within a few blocks is also fairly easy on Sunday mornings.
Each workshop is $40, which covers the instruction, the space, and the model. Class size is limited to 12, and a supply list will be emailed to you upon registration. I would love to see you there! To register, go to the sign-up page here, or click on the image above.
Wednesday, February 25, 2015
Learning about Rock Groups and The Rock Cycle

We started our learning by reading The Magic School Bus Rocky Road Trip Chapter Book. As we read this book, we learnt about different famous rock structure such as The Grand Canyon as well as Uluru (Ayers Rock). We later completed a lap book based on this book (details at the end of this post).

We continued our learning about rocks by going rock collecting. We collected different rocks from a few different locations and looked at the differences between them. We found that the rock we had collected from the beach we smooth and round due to the weathering from the waves where as the rocks we found near a lake were very sharp and rough.

We talked about the effects that weathering and erosion has on rocks and soil and how it helps rocks change. We watched this short YouTube clip on weathering and erosion to helped with our understanding and learning. We then started looking at the three different groups of rocks. I purchased this little rock kit from scholastic that has two samples of rocks from each of the three different rock groups. This gave us an idea of the different groups we were about to learn about.

Igneous Rock

Sedimentary Rock

Metamorphic Rock

The Rock Cycle

Lap book


Male nipples and round ligaments of the uterus
In men, however, the nipples serve no obvious function. They certainly have nothing to do with delivering milk. Lactation has never been observed in any healthy male mammal. I had to qualify that last statement with "healthy" because there are diseases, such as certain tumors of the pituitary gland, that can cause men to produce milk, an inconvenient condition called galactorrhea. An imbalance in the endocrine system can also cause gynecomastia, enlargement of the male breast. Still, these are rare exceptions to the rule. Nipples and breasts may have the potential to be useful in men, but in general they appear to be extraneous.
So why do we have them? Could male nipples be vestigial organs, evolutionary equivalents of the appendix? Darwin proposed that male mammals once shared the job of providing milk to their young. Its delightful conjecture, and not unreasonable, but it remains in the realm of just-so stories because (so far) there is no way to test its validity. If the story were true, you might expect the most anatomically primitive mammals - monotremes such as the duck-billed platypus and echidna - to have males with more highly developed nipples. In fact, we see the opposite: monotremes - male and female - have no nipples at all (but the females still lactate, expressing milk via little pores in the skin). Im only aware of a couple mammal groups in which the female has nipples and the male doesnt (a feature we might call "mammillary sexual dimorphism"): horses and rodents. If male nipples are on their way out, they sure are tenacious.
Whether or not male nipples are a relic of evolution, they are almost certainly a relic of development. In the earliest weeks following conception, the male and female embryo follow a virtually identical developmental trajectory. Then at about 7 weeks, the production of testosterone kicks in and the male diverges anatomically from the female. By then its too late: nipples have already formed in both sexes. Biologically its conceivable that random mutations could reverse the continued growth of the male nipple, causing it to involute and disappear completely by the time the baby boy is born, but apparently there hasnt been pressure for such mutations to take hold, if they have occurred. There are occasional mutations that lead to the absence of one or both nipples (in both males and females), but they are typically associated with other defects such as missing muscles and sweat glands and webbing of the fingers.
So are male nipples utterly useless? Its hard to respond with an unqualified "yes," because someone can always come up with something plausible. In some men the nipple may be considered an "erogenous zone," but what part of the male anatomy isnt? Even the appendix, the poster child of vestigial organs, isnt totally useless: it contains an abundance of lymphocytes and other cells that fight infection. Still, as many appendectomy patients can attest, we can live perfectly well without it. The same goes for nipples in men.*
In the interest of gender equity, what about women? Do women have anything similar to a male nipple, an essentially useless part of their anatomy that reflects a developmental constraint? In a classic (1987) and controversial essay called "Male Nipples and Clitoral Ripples," the late paleontologist Stephen Jay Gould argued that the clitoris, along with the female orgasm, fits the bill. The argument is further elaborated in a recently published book by biologist and philosopher of science Elisabeth A. Lloyd: The Case of the Female Orgasm: Bias in the Science of Evolution. Evidently she makes a good case (click here for a review), but lingering doubts are understandable. I suspect that the average woman places a much, much higher value on her clitoris than the average man places on his nipples.
Instead of weighing in on that controversy, Id like to propose a better female analogue of the male nipple: the round ligament of the uterus. The round ligaments are two slender ropes of connective tissue that run from the top of the uterus to the front side of the abdominal wall, pass through the inguinal canal (approximately at the level of the bikini line), and ultimately blend into the fatty connective tissue of the labia majora.
In the female fetus, you can trace the round ligament from the abdominal wall all the way up to the ovaries. At those early stages of development the round ligament is referred to as the gubernaculum, which means governor (same root as gubernatorial). The male fetus has a gubernaculum, too, except that its attached to testes, not ovaries. As the fetus grows, the role of the gubernaculum is similar in both the male and female: it gently guides the gonads (i.e., testes or ovaries) during their descent from their birthplace in the upper part of the abdomen. As they descend, the gubernaculum gets shorter.
There the similarities end. The testes have much farther to go. While the ovaries drop down into the relatively well-protected pelvic cavity (the space surrounded by the hip bones), the testes travel onward, punching a tunnel (i.e., the inguinal canal) through the abdominal wall and ending up suspended in an outpouching of the abdominal wall called the scrotum. Click here for a little animation of the testes squeezing through the abdominal wall (the greenish band is the gubernaculum).
The different fates of the ovaries and testes are reflected in the gubernaculum. In the male, each gubernaculum shortens as much as possible and leaves little or no remnant in the scrotum. In the female, the middle of the gubernaculum fuses with the top of the uterus, forming what appear to be two separate ligaments: (1) the ligament of the ovary, which connects the ovary to the uterus, and (2) the round ligament of the uterus, which connects the uterus to the abdominal wall. See the illustration below.
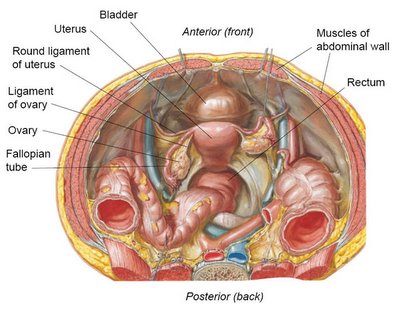 The ligaments of the ovary may serve a useful function: each one appears to maintain the proper distance between the ovary and the uterus, so that the fallopian tube can receive eggs from the ovary during ovulation.
But the round ligaments? As far as I can tell, theyre useless. One popular (and generally trustworthy) online resource (The Interactive Body Guide) suggests that the "round ligaments hold the uterus anteverted (inclined forward) over the urinary bladder." Seems reasonable, until you realize that something like 20-30% of women are born with a uterus that is retroverted (inclinded backward). The retroverted configuration is considered a perfectly normal variation that has no effect on fertility. In other words, the round ligaments arent very good at holding the uterus forward because theres no good reason for them to be.
Not only are round ligaments unnecessary, they can be a real pain - literally. As the uterus grows during pregnancy, the round ligaments stretch like rubber bands and tug on the abdominal wall, often causing round ligament pain. Fortunately the pain can usually be relieved with simple measures such as a hot bath, a shift of body position, or Tylenol. Like male nipples, the round ligaments of the uterus are relatively minor anatomical flaws, and any inconvenience they cause pales in comparison to the many anatomical marvels of the human body.
*More resources on male nipples:
- Why Do Men Have Nipples? A hilarious article from Salon.com.
- Why Do Men Have Nipples? A classic Q&A from The Straight Dope.
- Why Do Men Have Nipples? Hundreds of Questions Youd Only Ask a Doctor After Your Third Martini I havent read it yet, but its on my wish list.
The Dorsal Forearm Part 3 The Final Chapter
By the way, if you are interested in reading about the less complex tendinous landmarks of the ventral forearm, check out the very first post, The Ventral Forearm: What are those Tendons?
So. When we last left off in our forearm saga, we were looking at, among other structures, the "twin muscles," two muscles that look very much alike and run directly down the dorsal side of the forearm. Their similarity to one another as well as their central location on the dorsal forearm make them among the easiest to identify in this area.
The last three muscles well cover on the dorsal forearm can be found just radial to the twins-- meaning closer to the thumb side of the arm compared to the centrally located twins. Its no coincidence that each of these three muscles have the root "radial" in their names. As well as indicating that these muscles are found on the radial side of the arm, this root also tells us that these muscles pull the hand toward that side. This movement is known as abduction of the hand. Hence the fact that radial side arm muscles tend to abduct.

 |
| Key: Tlat: triceps, lateral head; Tten: triceps tendon; BrR: brachioradialis; ECRL: extensor carpi radialis longus; ECRB: extensor carpi radialis brevis; LE: lateral epicondyle; Anc: anconeus; OP: olecranon process; ED: extensor digitorum; EDM: extensor digiti minimi; ECU: extensor carpi ulnaris; FCU: flexor carpi ulnaris; APL: abductor pollucis longus; EPB: extensor pollucis brevis; EPL: extensor pollucis longus |
The photo above shows a dorsal forearm and an abducted hand. Because radial side muscles abduct the hand, they will stand out more in this position than in any other. The easiest one to spot is extensor carpi radialis longus, as it stands out clearly right next to the lateral epicondyle. Notice its oblique course compared to the surrounding dorsal forearm muscles. Notice also that it and brachioradialis originate on the upper arm (unlike the twin muscles that originate at the lateral epicondyle of the humerus.)
At the distal end of the arm, you may also notice three smaller muscles, abductor pollucis longus, extensor pollucis brevis, and extensor pollucis longus. While these muscles stand out clearly here, they often dont. We will look at them more closely later. You may remember, however, that we have already observed their tendons (which can be seen at the base of the thumb) in the post on the dorsal hand.
Ive also pointed out the lateral head of the triceps and the triceps tendon, structures on the posterior upper arm. We will cover these later, but this photo shows them very clearly.
Now lets take a look at this arm without the structure overlay:


Parts of the LARYNGEAL CAVITY
The boundaries formed by the vestibular and vocal folds divide the cavity of the larynx into three parts. These are illustrated schematically in the Figure below:
1. The VESTIBULE, which is the area above the vestibular folds.
2. The VENTRICLE, which is a pocket-like recess between the vestibular and vocal folds on both sides.
3. The INFRAGLOTTIC CAVITY, which is the area below the vocal folds.

There are two other terms you must know:
1. The GLOTTIS is the aperture formed by the vocal folds (analogous to the iris of the eye).
2. The RIMA GLOTTIDIS is the opening between the vocal folds (analogous to the pupil of the eye). Realize that the size of the rime glottidis is a major factor in determining how much air can enter the trachea and lungs.